Doc Robinson

Forum Replies Created
-
AuthorPosts
-
Doc Robinson
Participant@ my parents said know
The original version of that Salk article can still be found at the Internet Archive.
Original:
“Scientists have known for a while that SARS-CoV-2’s distinctive “spike” proteins help the virus infect its host by latching on to healthy cells. Now, a major new study shows that they also play a key role in the disease itself…”
https://web.archive.org/web/20210430171112/https://www.salk.edu/news-release/the-novel-coronavirus-spike-protein-plays-additional-key-role-in-illness/Revised
“Scientists have known for a while that SARS-CoV-2’s distinctive “spike” proteins help the virus infect its host by latching on to healthy cells. Now, a major new study shows that the virus spike proteins (which behave very differently than those safely encoded by vaccines) also play a key role in the disease itself.”The novel coronavirus’ spike protein plays additional key role in illness
ParticipantupstateNYer: “The spike protein debacle is EXACTLY what Dr. Sucharit Bhakdi has described as the consequence of the injections for months now.”
Back in early December, before the FDA issued the first EUA for the vaccines, a pediatric doctor at UCLA warned the FDA about the potential harm the spike proteins could cause.
“Before any of these vaccines are approved for widespread use in humans, it is important to assess in vaccinated subjects the effects of vaccination on the heart (perhaps using cardiac MRI, as Puntmann et al. did). Vaccinated patients could also be tested for distant tissue damage in deltoid area skin biopsies, as employed by Magro et al. As important as it is to quickly arrest the spread of the virus by immunizing the population, it would be vastly worse if hundreds of millions of people were to suffer long-lasting or even permanent damage to their brain or heart microvasculature as a result of failing to appreciate in the short-term an unintended effect of full-length spike protein-based vaccines on these other organs.”
“In caring for children with MIS-C, I have been impressed with how widespread the organ involvement is,
particularly given the absence of actively replicating virus in virtually all patients. Particular caution will be
required with regard to the potential widespread vaccination of children before there are any real data on the
safety or effectiveness of these vaccines in pediatric trials that are only now beginning.”The FDA issued the EUA for the Pfizer injections a few days after they received this letter. The letter has so much relevant information that I am including it below.
Comment from J. Patrick Whelan MD PhD
Posted by the Food and Drug Administration on Dec 8, 20208 December 2020
U.S. Food and Drug Administration
Vaccines and Related Biological Products Advisory CommitteeRE: Notice of Meeting; Establishment of a Public Docket; Request for Comments related to consideration of vaccines against SARS-CoV-2
Dear Colleagues,
I am a pediatric specialist caring for children with the multisystem inflammatory syndrome (MIS-C). I am concerned about the possibility that the new vaccines aimed at creating immunity against the SARS-CoV-2 spike protein (including the mRNA vaccines of Moderna and Pfizer) have the potential to cause microvascular injury to the brain, heart, liver, and kidneys in a way that is not currently being assessed in safety trials of these potential drugs.
Puntmann et al. (JAMA Cardiol. 2020;5:1265-1273) showed that the prospective study of 100 German patients who were recently recovered from COVID-19 revealed significant cardiac involvement on cardiac MRI scans in 78% of them, an average 2-1/2 months after their recovery from the acute illness. Two-thirds of these patients were never hospitalized, and there was ongoing myocardial inflammation in 60%. The abnormalities occurred independent of preexisting conditions, severity of the initial disease, and overall course of the acute illness.
Magro et al. showed that there is complement-mediated damage even in grossly normal skin of coronavirusinfected individuals (Human Pathology 2020:106:106-116). They have also shown (Magro et al. Annals of Diagnostic Pathology 2021:50 in press ) that ACE-2 receptor expression is highest in the microvasculature of the brain and subcutaneous fat, and to a lesser degree in the liver, kidney, and heart. They have further demonstrated that the coronavirus replicates almost exclusively in the septal capillary endothelial cells of the lungs and the nasopharynx, and that viral lysis and immune destruction of those cells releases viral capsid proteins (or pseudovirions) that travel through the circulation and bind to ACE2 receptors in these other parts of the body – leading to mannan-binding lectin complement pathway activation that not only damages the microvascular endothelium but also induces the production of many pro-inflammatory cytokines. Meinhardt et al. (Nature Neuroscience 2020, in press) show that the spike protein in brain endothelial cells is associated with formation of microthrombi (clots), and like Magro et al. do not find viral RNA in brain endothelium. In other words, viral proteins appear to cause tissue damage without actively replicating virus.
Is it possible the spike protein itself causes the tissue damage associated with Covid-19? Nuovo et al (in press) have shown that in 13/13 brains from patients with fatal COVID-19, pseudovirions (spike, envelope, and membrane proteins) without viral RNA are present in the endothelia of cerebral microvessels. Furthermore, tail vein injection of the full length S1 spike subunit in mice led to eurologic signs (increased thirst, stressed behavior) not evident in those injected with the S2 subunit. The S1 subunit localizes to the endothelia of microvessels in the mouse brain, and is a potent neurotoxin. So the spike S1 subunit of SARS-CoV-2 alone is capable of being endocytosed by ACE2 positive endothelia in both human and mouse brain, with a concomitant pauci-cellular microencephalitis that may be the basis for the neurologic complications of COVID19. The Pfizer/BioNTech vaccine (BNT162b2) is composed of an mRNA that produces a membrane-anchored full-length spike protein. The mouse studies suggest that an untruncated form of the S1 protein like this may cause a microvasculopathy in tissues that express much ACE2 receptor. A truncated form of S1 was much less damaging in mice.
While there are pieces to this puzzle that have yet to be worked out, it appears that the viral spike protein that is the target of the major SARS-CoV-2 vaccines is also one of the key agents causing the damage to distant organs that may include the brain, heart, lung, and kidney. Before any of these vaccines are approved for widespread use in humans, it is important to assess in vaccinated subjects the effects of vaccination on the heart (perhaps using cardiac MRI, as Puntmann et al. did). Vaccinated patients could also be tested for distant tissue damage in deltoid area skin biopsies, as employed by Magro et al. As important as it is to quickly arrest the spread of the virus by immunizing the population, it would be vastly worse if hundreds of millions of people were to suffer long-lasting or even permanent damage to their brain or heart microvasculature as a result of failing to appreciate in the short-term an unintended effect of full-length spike protein-based vaccines on these other organs.
In caring for children with MIS-C, I have been impressed with how widespread the organ involvement is, particularly given the absence of actively replicating virus in virtually all patients. Particular caution will be required with regard to the potential widespread vaccination of children before there are any real data on the safety or effectiveness of these vaccines in pediatric trials that are only now beginning.
Patrick Whelan MD PhD
UCLA Pediatric Rheumatology
Los Angeles CA 90095ParticipantNoirette: “Vax, wow super! 100% efficacity! Because only 4 – four! Out of 3,700 adolescents ‘got covid’ – > .all the 4 were in the placebo group.”
As I noted in yesterday’s comments, when the definition of “case” was changed from that vaccine trial’s definition to the CDC’s definition, there were a number of Covid cases in both groups (vaccinated and placebo). So goodbye to the “100% efficacy.”
And despite all the headlines touting “100% effective” (based solely on a slanted press release from Moderna), the absolute risk reduction is probably only 0.3% or less.
ParticipantSorry folks, I made a math error in my comment above. Please disregard the part after “To put this 93% efficacy into perspective…”
ParticipantModerna Will Seek Authorization For Teen Covid Vaccine After Trial Shows 100% Efficacy (Forbes)
The news stories about this are just parroting the very limited (and slanted) information presented in the press release from Moderna, which I’ll try to make some sense of, below.
3,732 adolescent participants ages 12 to less than 18 years were enrolled and randomized 2:1 to two 100 µg doses of mRNA-1273 or placebo. The primary endpoint of non-inferior immunogenicity versus the Phase 3 adult study comparator group was met. After two doses, no cases of COVID-19 were observed in the vaccine group using the case definition from the adult Phase 3 COVE study, compared to 4 cases in the placebo group, resulting in a vaccine efficacy of 100% starting 14 days after the second dose. Because the incidence rate of COVID-19 is lower in adolescents, a secondary case definition based on the CDC definition of COVID-19 was also evaluated to include cases presenting with milder symptoms. Using the CDC definition, which requires only one COVID-19 symptom and a nasopharyngeal (NP) swab or saliva sample positive for SARS-CoV-2 by RT-PCR, a vaccine efficacy of 93% after the first dose was observed.
Of the 3,732 adolescents,
2,488 were given the mRNA injections
1,244 were given the placeboUsing the case definition for adults (not adolescents), there were no Covid cases in the vaccinated group, and 4 cases in the placebo group. 4 cases out of 1,244 is less than one percent, actually less than a third of one percent. So the Absolute Risk Reduction for adolescents is only around a third of one percent (when using the case definition for adults).
Using the more appropriate case definition for adolescents, there were an undisclosed number of Covid infections in the vaccine group, resulting in the reported 93% efficacy after the first dose. To put this 93% efficacy into perspective, if 14 vaccinated people were infected, and 7 unvaccinated people were infected, the efficacy would be zero percent (because there are twice as many vaccinated people in the study, giving both groups an equal percentage of infections.) If we tweak this a tiny bit, and there are 13 cases in the vaccinated group (instead of 14 cases), and the same 7 cases in the unvaccinated group, the vaccine efficacy would be 93%.
So with only a couple thousand participants, a small tweaking of the numbers (using different case definitions, or test thresholds, etc.) can make the vaccine efficacy go from zero percent to 93%.
ParticipantThe vaccine biodistribution is not just an issue with the mRNA injections, it is relevant for viral vector vaccines like J&J and AZ/Oxford,
Although, the modern viral vectors that are used in CoViD vaccines are silenced (replication-deficient), each dose of the vaccine contains a very high viral load (e.g., 50 billion viral particles per dose in Ox/AZ or J&J/Janssen CoViD-19 vaccines whereas 100 billion viral particles per dose in the Sputnik-V). The viral particles are unlikely to be confined to the muscles at the injection site; they are free to distribute across the body and drain through the lymphatic system; their apparent volume of distribution is likely to be very high. The biodistribution of ChaAdOx1 [AZ/Oxford] containing HBV in BALB/c mice (study 0841MV38.001) indicated the highest viral levels at the injection site, but low levels of virus were still detected after 24 hours of injection in all other tissues (including blood, brain, heart, inguinal lymph node, kidney, liver, lung, gonads, and spleen). The proportional tissue distribution of viral vectors in the body tissues away from the injection site was likely to increase with time, however, biodistribution beyond 24h post-dose was not studied. The biodistribution of ChAdOx1 [AZ/Oxford] encoding nCoV-19 following intramuscular injection in mice (study 514559) was ongoing at the time of its regulatory approval [4]. The study 514559 was aimed to examine the biodistribution of ChAdOx1 [AZ/Oxford] nCoV-19 in bone marrow, brain, spinal cord, sciatic nerve, and other body tissues. The data from this study is not yet available in the public domain but this might provide evidence of vaccine delivery in the brain. We, therefore, agree with your comments that all vaccine-related data and analyses in possession of the regulatory authorities must be published in full without any further delays.
However, in the absence of the results of study 514559, the biodistribution of ChaAdOx1 [AZ/Oxford] HBV in mice (study 0841MV38.001) confirms the delivery of vaccine into the brain tissues. The vaccine may therefore spur the brain cells to produce CoViD spike proteins that may lead to an immune response against brain cells, or it may spark a spike protein-induced thrombosis. This may explain the peculiar incidences of the fatal CVST observed with viral vector-based CoViD-19 vaccines.
https://www.bmj.com/content/373/bmj.n958/rr-1
Regarding the “50 billion viral particles per dose in Ox/AZ or J&J/Janssen CoViD-19 vaccines…”
Trying to put “50 billion viral particles per dose” into numerical perspective, the human liver consists of an estimated 361 billion cells (and it’s reportedly the body’s largest and heaviest internal organ.)
ParticipantBritish Medical Journal – “Covid-19 vaccines: In the rush for regulatory approval, do we need more data?”
From that article (linked by Germ, above):
“Pfizer and Moderna did not respond to The BMJ’s questions regarding why no biodistribution studies were conducted on their novel mRNA products, and none of the companies, nor the FDA, would say whether new biodistribution studies will be required prior to licensure.”Meanwhile, this was published in the same British Medical Journal on 15 April 2021:
For COVID-19 mRNA Vaccine (Pfizer or Moderna), the biodistribution studies in animals were not conducted. The surrogate studies with luciferase and solid-lipid nanoparticles (Pfizer) confirm a biodistribution to the liver and other body tissues beyond the administration site [5]. For Moderna, the biodistribution of mRNA-1647 (encoding CMV genes) formulated in a similar lipid nanoparticulate delivery system confirms a biodistribution beyond the injection site, in particular, the distribution to the lymph nodes, spleen and the eye was noted [6]. However, the detailed tissue-specific distribution of mRNA vaccines encoding SARS-CoV-2 spike proteins (Pfizer or Moderna) is not fully known that can offer invaluable insights into the potential safety of these vaccines in peoples with pre-existing conditions or those on certain medications.
The detailed biodistribution data including pharmacokinetics of various CoViD vaccines were not conducted by the vaccine manufacturers because the studies demonstrating biodistribution of antigens were considered ‘not required’ by the regulatory authorities on the premise that vaccines work by an immunological response than the classic pharmacological approach. However, such an exemption may barely justify the conventional vaccines such as those incorporating whole inactivated virus, split virion, or the sub-unit vaccines, that directly attracts an immune response post-injection.
On the contrary, modern genetic vaccines work on the premise of gene delivery, therefore, a detailed biodistribution and pharmacokinetic evaluation of the formulated product is invaluable in understanding the potential impact of vaccine encoding gene transfection to various body tissues beyond the site of injection.
Might post-injection distribution of CoViD vaccines to the brain explain the rare fatal events of cerebral venous sinus thrombosis (CVST)?
https://www.bmj.com/content/373/bmj.n958/rr-1ParticipantIsrael to end COVID-19 restrictions after vaccine success (Reuters)
“…the restrictions and the Green Pass system will be revoked from the start of June.”It will be interesting to see if Geert Vanden Bossche is right. He is still expecting a surge to occur in Israel within a month from now.
Q:
“How can it be explained that in Israel it seems that the massive vaccination has almost stopped the pandemic and no dramatic effects are being observed over people that have been vaccinated?”A:
“It’s just a matter of weeks for a surge in Israel to occur due to resistance of the virus to vaccinal antibodies in vaccinees. I expect this surge to occur before summer.”ParticipantGerm: “It is critical to think about Covid-19 as an endothelial dysfunction, including in long haulers.”
In addition to endothelial dysfunction, there’s evidence that long-haul Covid may result from “long-lasting changes in baseline genetic expression” in epithelial cells, induced by “exposures to the viral spike protein.”
This study looked at the effects of Covid spike protein (not the entire virus). Using “cell culture technique to simulate the physiological conditions in the lung airway in vitro,” the epithelial cells were exposed to the spike protein for only 4 hours. After a two day “recovery”, the cells were examined. Note that the conclusions are about exposure to just the spike protein (which is relevant to the vaccines).
Conclusions
Our preliminary results suggest that the SARS-CoV-2 spike protein is enough to change the baseline protein expression in primary HBECs. After recovery, genes related to immune response retained changes in gene expression, and these may indicate relevant long-term effects in asymptomatic patients. Additionally, the interplay between immune response and other pathways after SARS-CoV-2 spike protein exposure should be investigated in the future.SARS-Cov-2 Spike Protein Changes Genetic Expression in Human Primary Bronchial Epithelial Cells…
https://faseb.onlinelibrary.wiley.com/doi/abs/10.1096/fasebj.2021.35.S1.03097The final line:
“Additionally, the interplay between immune response and other pathways after SARS-CoV-2 spike protein exposure should be investigated in the future.”I think this should have been investigated fully before authorizing the widespread use of spike protein-based vaccines. I wonder whether “long-haul adverse reactions” from the Covid vaccines will show up and be acknowledged, or whether they will be downplayed and attributed to an asymptomatic Covid infection that wasn’t noticed earlier.
ParticipantInsufficient Sleep Impairs T-Cell Response to SARS-CoV-2
The average sleep duration was 7 h 33 min during normal habitual sleep, and 6 h (± 38 min) during sleep restriction.
https://www.atsjournals.org/doi/pdf/10.1164/ajrccm-conference.2021.203.1_MeetingAbstracts.A1107
ParticipantV. Arnold: “…any idea where that Buddha statue is located?”
If you travel by train on the Meitetsu line from Nagoya to Inuyama (the place of one of the most beautiful Japanese castles), while passing through the Konan City, if you look to the left, you may catch a glimpse of a very original daibutsu (great Buddha).
Built at the edge of a neighborhood, it is called Hotei Daibutsu, but the name is misleading, because the statue does not represent the god Hotei – its name comes from the nearby train station… Actually, the statue represents the Amida Buddha (Amida Nyorai in Japanese) and it’s impressive because of its unusual face.
https://muza-chan.net/japan/index.php/blog/unusual-statue-hotei-daibutsu-konan-city

 Participant
Ohio will give 5 people $1 million each in COVID-19 vaccine lottery
Something for the “vaccine hesitant” to think about:
In the vaccine lottery, the chance of dying from the vaccine is actually greater than the chance of winning a million dollars.ParticipantGerm: “The vaccine spike DOES shed into the blood and is detectable…y
What strikes me about that study, besides the fact that the (potentially harmful) spike proteins were confirmed to be circulating in the bloodstream following the mRNA injection, is the uncertainty about why the spike proteins are there.
“We hypothesize that the cellular immune responses triggered by T-cell activation, which would occur days after the vaccination, lead to direct killing of cells presenting spike protein and an additional release of spike into the blood stream. The mechanisms underlying release of free S1 and the subsequent detection of the intact spike protein remain unclear and require further studies.“
Participantphoenixvoice: “it will be hard to hide that the vaccinated are more susceptible to severe Covid than the unvaccinated…”
I think those are good points, yet they would try to hide it anyway.
Getting almost everyone vaccinated could effectively hide it.As in, ““Compulsory shots are unpalatable, but may be necessary.”
ParticipantPolder Dweller: “… the scientists will be running around trying to think up ways to head off ADE in the vaccinated.”
I anticipate that any news of the ADE will be suppressed, the new wave of severe infections will be attributed to a “new variant” of Covid, and the evolution of the “new variant” (with all the resulting deaths) will be blamed on all those selfish “anti-vaxxers” who refused to take the injections when they should have, and the “solution” offered will be more rounds of new and improved injections.
Participant“The new artificial intelligence (AI) technology, called Safe Entry Stations…”
The medical scanner booths use AI to determine whether “the individual is either safe (green light) or a potential risk (red light).” All that’s missing (?) is facial recognition software.

Screens for 7 Symptoms in Seconds.
Fever
Cough
Exhaustion
Congestion
Sweat Gland Activation
Eye Redness
HeadacheMulti-spectrum cameras paired with prorietary AI provides checks for multiple sympsoms, concluding the individual is either safe (green light) or a potential risk (red light).
Highly customizable, can easily be integrated into existing décor and lobbies with specialized finishing.
…
720 SCANS PER HOUR
Near-Real time screening
…
MEDICALLY BASED
Uses proprietary AI to measure a grouping of symptoms determined by a medically based algorithm
…
Frequently Asked Questions
How does the Safe Entry Station work?
Will I show “positive” with a common cold or flu?
How long does the system take to process a scan?
How does the tech respond to people who are completely asymptomatic:
What symptoms does Safe Entry screen for?
Does the system require installation of any other hardware ?
How does the PredictMedix software different than other fever scanners on the market?
How Accurate is the technology?
Will I feel anything while walking through the unit and being scanned?
What kind of internet bandwidth is required for the Safe Entry Station?
How is my privacy protected?Participantfrom zerosum’s link:
“Media Bias / Fact Check”
The Automatic Earth
LEFT-CENTER BIAS
These media sources have a slight to moderate liberal bias. They often publish factual information that utilizes loaded words (wording that attempts to influence an audience by using appeal to emotion or stereotypes) to favor liberal causes. These sources are generally trustworthy for information, but may require further investigation.Factual Reporting: HIGH
Notes: The Automatic Earth is a financial news website. TAE is different than most financial websites in that they oppose the hoarding of wealth and criticize bankers. All information on the website is sourced to credible information. When curating news from other sources most fall on the left-center of the political spectrum. Overall, we rate this site left-center for bias and factual in reporting. (D. Van Zandt 6/3/2017)
ParticipantIn the US (as well as the UK), death numbers have been down for more than two months. The CDC graphs show that the total deaths from all causes have been below the threshold for excess deaths since the week ending March 13. (This even includes additional death “predictions” added to the reported death numbers to account for incomplete records in recent weeks.)
https://www.cdc.gov/nchs/nvss/vsrr/covid19/excess_deaths.htm
ParticipantGerm: “Here in the UK, far, far, far, fewer people are dying than normal…
You’d think that would be all over the news.”With more than two months of below-normal death rates, you’d think there would be celebrations.
From that linked UK statistics site:“This is the ninth consecutive week that deaths have been lower than the five-year average in England.”
ParticipantFrom the “Probability and Risk” article (linked by Germ) which examines the numbers in the Israel study (the study where 8 of the co-authors are investors in Pfizer):
https://probabilityandlaw.blogspot.com/2021/05/important-caveats-to-pfizer-vaccine.html
So, the number of ‘cases’ per 1000 tests were:
30.8 for unvaccinated people…
7.5 for vaccinated people…Looking at it this way, the unvaccinated people were 4 times more likely to test positive for Covid, compared to the vaccinated people. (However, with the infection rate being so low, many of the positive test results were probably false positives.)
It is likely that most of the positives among the asymptomatics were false positives. This is because, especially at times when the infection rate is low, a false positive PCR test rate of, say just 0.4%, would still mean that the majority of positive tests among asymptomatics are false.
If we apply the test results, without considering the number of false positive tests, then one unvaccinated person at a restaurant would be as “dangerous” as a table of four vaccinated people (considering that the vaccines don’t stop transmission).
30.8 positive tests per 1000 =
3% chance of a positive test result for the unvaccinated (during the 2+ month study).7.5 positive tests per 1000 = 0.75% =
almost 1% chance of a positive test result for the vaccinated (during the 2+ month study).But, this doesn’t consider just how low the Covid risks are, vaccinated or not. The positive test results were obtained during a study which lasted more than 2 months. The chance of a positive test result on any specific date is much lower. Furthermore, the chance of a person with a positive test result ending up with severe illness or death from Covid is much, much lower. And this doesn’t even look at the other part of the picture, the chances of getting a serious adverse reaction from the vaccines.
It is also worth noting that, even if we ignore all of the above issues and accept as undisputed the number for ‘COVID-19 related deaths’ in the Israel study (715 among the unvaccinated and 138 among the vaccinated), then the absolute percentage increase in risk of death for an unvaccinated person is just 0.036%. That means that, even if we accept the 95% effectiveness measure, for every 10,000 unvaccinated people, about 3 or 4 would die as a result of not being vaccinated. And this brings us to the final (and critical) problem with the study. It does not provide any information about the number of adverse reactions – in particular the number of deaths – due to the vaccine. Hence, it does not provides the necessary information to make an informed decision about the overall risk/benefit of the vaccine.
Participant@ gardenpath, that’s the work of Andrew Bostom, MD
Participantlaffin_boy: “A link to the source of your lead-off entry (covid-19 vaccine risk-benefit data for those under 18-years old ) please”
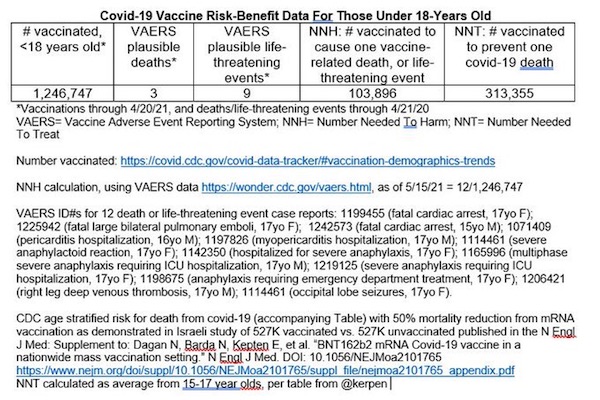
That’s the work of Andrew Bostom, MD
Participant• Covid-19 Testing Turns To T Cells (Nature)
Does this address only vaccine-related T cells?The T-Detect test is reportedly based on “extensive genomic characterization of the T-cell repertoires of people infected with SARS-CoV-2.” This should address all of the T-cell responses to a Covid infection, not just the vaccine-related responses.
The test emerged from a longstanding collaboration between Adaptive and Microsoft to apply machine learning to define the ‘rules’ according to which T-cell receptors (TCRs) identify their cognate antigens. That, combined with extensive genomic characterization of the T-cell repertoires of people infected with SARS-CoV-2, allowed Adaptive to define a broad set of TCRs that are indicative of infection with the virus. The test sequences the total TCR repertoire present in a given sample and then calculates the relative enrichment for SARS-CoV-2–specific TCRs compared with predefined thresholds to determine the result, taking into account variation in individuals’ immune responses.
https://www.nature.com/articles/s41587-021-00920-9
As I mentioned in an earlier comment, the T-Detect test is being marketed directly to the public, with online ordering and no involvement of one’s doctor. The article in Nature says the “samples can be shipped at room temperature”, since they are “looking at the genomic DNA of T cells” instead of needing live cells for the tests.
ParticipantThe T-cell immunity test which John Day mentioned can be ordered online, without getting your doctor involved.
Special self-pay test price $150
Additional fees include test authorization ($9) and blood draw (on-site lab: $60 or in-home: $140).
…
The T-Detect COVID test is currently not covered by health insurance. The T-Detect COVID test is FSA/HSA eligible.ParticipantMore about the breakthrough cases not being reported by the CDC:
CDC Limits Review of Vaccinated but Infected; Draws Concern
…
But tracking and sequencing the cases helps in figuring out who may be more at risk, whether new variants evade the vaccines and when protection from the shots begins to wane. At the same time, those infected — some of whom are suffering widespread medical issues, even if they’re not hospitalized — say they feel lost as a result of the lack of information.“We shouldn’t be narrowing the focus, we should be broadening and develop a systematic plan,” said Eric Topol, director of the Scripps Research Translational Institute in La Jolla.
…
At the end of April, more than 9,000 Americans were reported to be infected after being vaccinated, according to the U.S. Centers for Disease Control and Prevention… The CDC says its numbers are probably an undercount, since their surveillance system is passive and relies on voluntary reporting from state health departments that may not be complete.
…
Michael Kinch, a former drug developer who’s now associate vice chancellor at Washington University in St. Louis, says as much information as possible should be recorded on breakthroughs. Cases that don’t rise to hospitalization are still important to track, he said, since symptoms that aren’t as severe for someone could eventually lead to hospitalizations. Non-life-threatening symptoms can impact someone’s life greatly, and evolve over time, Kinch said. “It’s essential that we stay on top of this,” he added.ParticipantVanden Bossche expects a surge in Covid cases in Israel before summer.
These would be “breakthrough cases” of course. However, what happens if the breakthrough cases aren’t reported unless the patient is hospitalized or dies? The surge would be there, but we wouldn’t know it by looking at the government’s numbers. But the government will report all the Covid cases, whether or not they are breakthrough cases, right?
Not in the US. Effective today, the CDC will only report the number of breakthrough cases which result in hospitalization or death. WTF? How does it make sense that if you get a Covid case and aren’t hospitalized, the case is counted if you weren’t vaccinated, but not counted if you were vaccinated?
COVID-19 Breakthrough Case Investigations and Reporting
As previously announced, CDC is transitioning to reporting only patients with COVID-19 vaccine breakthrough infection that were hospitalized or died to help maximize the quality of the data collected on cases of greatest clinical and public health importance. That change in reporting will begin on May 14, 2021.
https://www.cdc.gov/vaccines/covid-19/health-departments/breakthrough-cases.htmlParticipantVanden Bossche expects a surge in Covid cases in Israel before summer.
How can it be explained that in Israel it seems that the massive vaccination has almost stopped the pandemic and no dramatic effects are being observed over people that have been vaccinated?
It’s just a matter of weeks for a surge in Israel to occur due to resistance of the virus to vaccinal antibodies in vaccinees. I expect this surge to occur before summer.
Participant“Another would discharge student debt in the event of a debtor’s death.”
Federal student loans (in the US) are already forgiven/discharged if the student dies, but private lenders can require co-signers for student loans, which would contractually put parents (or others) on the hook if the student dies.
https://www.forbes.com/advisor/student-loans/what-happens-to-student-loans-when-you-die/
ParticipantI was looking for an update about Covid cases & deaths in Texas, and found this article from May 12 in The New York Times, of all places (it’s a guest essay from a writer in Texas).
Are We Following the Science or Our Tribes?
by Carrie McKeanA few weeks ago, my 10-year-old daughter, Cora, and I walked into an indoor trampoline park. Resuming full-scale kid birthday parties became socially acceptable here in West Texas months ago, but this was our first time back indoors like that. Though many of us were vaccinated, none of the guests wore masks, the place appeared to be at full capacity, and kids were laughing and playing together like it was 2019 again.
Depending on your ZIP code, this tale may make you shrug or shriek.
…
Now with the arrival of spring, the general feeling in town is decidedly prepandemic. Some locals joke that while the pandemic might not be over, we’re over the pandemic. Texas lifted mask mandates and other restrictions on March 10. A few weeks later Gov. Greg Abbott trumpeted results some liberals thought were impossible: “Today the 7-day Covid positivity rate dropped to a new recorded low: 4.95 percent,” he said in a tweet. “Hospitalizations dropped to a 6 month low.”
…
Though I’m vaccinated, many people I know are not, and it’s not because they’ve all fallen for fringe conspiracy theories. Many remain unconvinced that vaccine safety can be assured, given the compressed development timeline — choosing to bet on Covid’s high survivability rate rather than voluntarily injecting themselves with something they see as pushed by Big Government.
…
In our community, many of us have been back to in-person school and work for several months. Some people wary of variants are still choosing to stay mostly at home, but many aren’t. Both options are socially acceptable.
…
“You’re going to love living here,” [10-year-old] Cora told the new girl on our street. “It’s like coronavirus never even happened.”Participant• Merriam-Webster: ‘Anti-Vaxxer’ Now Includes Those Who Oppose Forced Jabs (RT)
I don’t agree with that definition, but it’s been that way since the Internet Archive first recorded Merriam-Webster’s definition of “anti-vaxxer” in 2018.
Definition of anti-vaxxer
: a person who opposes vaccination or laws that mandate vaccinationhttps://web.archive.org/web/20181125060933/https://www.merriam-webster.com/dictionary/anti-vaxxer
ParticipantCorrection: 12-15 year-old children.
ParticipantYesterday, the FDA decided to allow the Pfizer injections for 12-17 year-old children, and this decision was made before the FDA advisory committee meeting (on June 10) to discuss “Pediatric Use of COVID-19 Vaccines.”
FDA In Brief: FDA to Hold Meeting of its Vaccines and Related Biological Products Advisory Committee to Discuss Pediatric Use of COVID-19 Vaccines
https://www.fda.gov/news-events/press-announcements/fda-brief-fda-hold-meeting-its-vaccines-and-related-biological-products-advisory-committee-discussParticipantI looked at the FDA’s justification for their decision to extend the Pfizer EUA to adolescents (age 12-15), and what struck me was the small amount of data they have. Only as few as 566 (or so) children were monitored, and for possibly less than 3 months, after getting the second injection. “At least 2 months” doesn’t give much reassurance about potential long-term effects in growing children.
FDA Evaluation of Available Safety Data
The available safety data to support the EUA in adolescents down to 12 years of age, include 2,260 participants ages 12 through 15 years old enrolled in an ongoing randomized, placebo-controlled clinical trial in the United States. Of these, 1,131 adolescent participants received the vaccine and 1,129 received a saline placebo. More than half of the participants were followed for safety for at least two months following the second dose.
The most commonly reported side effects in the adolescent clinical trial participants, which typically lasted 1-3 days, were pain at the injection site, tiredness, headache, chills, muscle pain, fever and joint pain.
Participantphoenixvoice: “…the usual process for bringing a vaccine to market”?
Before Covid, the fastest vaccine development took 4 years, and that was for mumps in the 1960s. Every other vaccine took longer than 4 years.
The fastest vaccine in history
December 10, 2020The COVID-19 vaccines coming soon to the United States and already approved in the U.K. and Canada are the fastest vaccines ever created.
In a remarkable achievement of medical science, we’ve gone from identifying a new pathogen — the novel coronavirus known as SARS-CoV-2 — to discovering an immune response against it to developing and testing a safe and effective vaccine for it in less than 12 months.
Previously, the fastest vaccine to go from development to deployment was the mumps vaccine in the 1960s, which took about four years.
https://connect.uclahealth.org/2020/12/10/the-fastest-vaccine-in-history/
ParticipantToday, former British ambassador and whistleblower Craig Murray was sentenced to 8 months in prison for reporting the same details of a court case which some mainstream news outlets had also published. He was the only one prosecuted.
His sentence conveniently prevents him from going “to Spain to testify in the criminal prosecution for the CIA spying on Assange’s legal team.” Some of Murray’s meetings with Assange in the Ecuadorian embassy were secretly recorded.
“Defence say Mr Murray is due to give evidence in a Spanish Court on May 20 on a Julian Assange related case. [Judge] Lady Dorrian says in that case they could begin the prison sentence on the 19th”
https://twitter.com/CraigMurrayOrg/status/1392127060164988930
Participantoxymoron: “Does anyone know if Omega 3 has any effect on health/recovery with regards to Covid?”
A study of 100 patients showed that a quarter of the patients, those having a higher “Omega-3 Index” in blood tests, were “were 75% less likely to die” than the other patients. “More well-powered studies are clearly needed.”
Blood omega-3 fatty acids and death from COVID-19: A pilot study
https://www.sciencedirect.com/science/article/pii/S0952327821000132Another study showed that “Omega-3 supplementation improved the levels of several parameters of respiratory and renal function in critically ill patients with COVID-19… The intervention group had significantly higher 1-month survival rate… Further clinical studies are warranted.”
The effect of omega-3 fatty acid supplementation on clinical and biochemical parameters of critically ill patients with COVID-19: a randomized clinical trial
https://translational-medicine.biomedcentral.com/articles/10.1186/s12967-021-02795-5Participant• World’s Most Vaccinated Country Sees Unprecedented Spike In Covid Cases (WaPo)
It’s interesting that among its warnings about the Covid vaccines, the Swiss Policy Research site says the spike in the Seychelles is most likely “a combination of the vaccination campaign spreading the virus (even into high risk groups), and people exposing themselves to higher risks prior to full protection.”
On another page, Swiss Policy Research says that “the process of mass vaccination – with millions of high-risk people visiting vaccination centers, or being visited by mobile vaccination teams, e.g. in nursing homes – might accelerate infections, and ultimately deaths, in high-risk groups, before full vaccine protection becomes effective.”
Participant• CDC Uses Different PCR Test Rules For Vaccinated, Non-Vaccinated (AVV)
I was verifying that at the CDC site and found this:
“CDC is transitioning to reporting only COVID-19 vaccine breakthrough infections that result in hospitalization or death”
So the CDC is not going to report the numbers of breakthrough cases which don’t lead to hospitalization or death. This sounds like a way to boost the public’s opinion of the effectiveness of the vaccines (since the vaccines allegedly reduce the severity of most breakthrough infections). It’s a bad idea because not only will it make it impossible for the public to assess the actual effectiveness of the vaccines, it will also be impossible to make public health decisions related to the actual numbers of vaccinated people who are breakthrough cases, potentially transmitting the virus to others.
As previously announced, CDC is transitioning to reporting only COVID-19 vaccine breakthrough infections that result in hospitalization or death to help maximize the quality of the data collected on cases of greatest clinical and public health importance. That change in reporting will begin on May 14, 2021. In preparation for that transition, the number of reported breakthrough cases will not be updated on May 7, 2021.
https://www.cdc.gov/vaccines/covid-19/health-departments/breakthrough-cases.html
Participant• Experts Say It’s Vital That Parents Get Their Kids Vaccinated For Covid (F.)
“By the last week of April, cases among children and teens accounted for more than 22% of new cases in the U.S, and there was a 4% increase in the total number of cases in kids. Almost 4 million kids have been diagnosed with Covid-19 since the beginning of the pandemic. Luckily, vaccines for kids are arriving soon.”What a load of alarmist propaganda bullsh*t.
Covid death rates for children and teens are still near-zero on the CDC charts, and even if they were to increase by 25%, 50%, 100%…, they would still be near-zero.
If this image posts, it shows the Weekly Covid Deaths (per 100,000) for each age grouping. The yellow lines (representing ages 0-17) aren’t even visible because they’ve been down near zero the whole time.

This next image, if it posts, shows the same graph with details I pulled up for the peak of the Covid deaths back in December, to try to show how high the numbers went for children and teens. They are still near-zero, while the 80+ age group is up at 69 deaths per 100,000:

You can see for yourself at the CDC site. Click on AGE under the DEATHS option.
https://covid.cdc.gov/covid-data-tracker/#demographicsovertimeParticipantRegarding the absolute risk reduction of the mRNA injections, and the resulting number of people that need to be vaccinated for one person to get some benefit, this was published in the British Medical Journal BMJ last year (from a retired pediatrician):
Moderna vaccine is nearly 95% effective, but…
There were 90 cases of Covid-19 illness in a placebo group of 15,000 (0.006) and 5 cases in a vaccine group of 15,000 (0.00033). This yields an absolute risk reduction of 0.00567 and NNTV = 176 (1/0.00567). There were 11 severe illnesses, all in the placebo group, for an absolute risk reduction of 0.00073 and NNTV = 1370. So to prevent one severe illness 1370 individuals must be vaccinated. The other 1369 individuals are not saved from a severe illness, but are subject to vaccine adverse effects, whatever they may be and whenever we learn about them.
How does this compare with other vaccines? Before the measles vaccine became available 90% of children in North America had measles by age 10. Two doses of the vaccine are about 95% effective, so a vaccinated individual’s risk is reduced by 0.855 (0.90 x 0.95), and the NNTV = 1.17 (1/0.855); this is extraordinarily effective.
https://www.bmj.com/content/371/bmj.m4471/rr-0
SUMMARY
Moderna mRNA injection:
To prevent one case of Covid, 176 people need to be injected (twice).
To prevent one severe case of Covid illness, 1370 people need to be injected (twice).Measles vaccine:
To prevent one case of measles, one child needs to be vaccinated.
(1.17 to be exact) -
AuthorPosts